Do They Put You to Sleep for Wisdom Teeth Removal?
You may stay awake, feel sleepy with sedation, or be unconscious under general anesthesia. Learn the differences and what to ask before surgery.
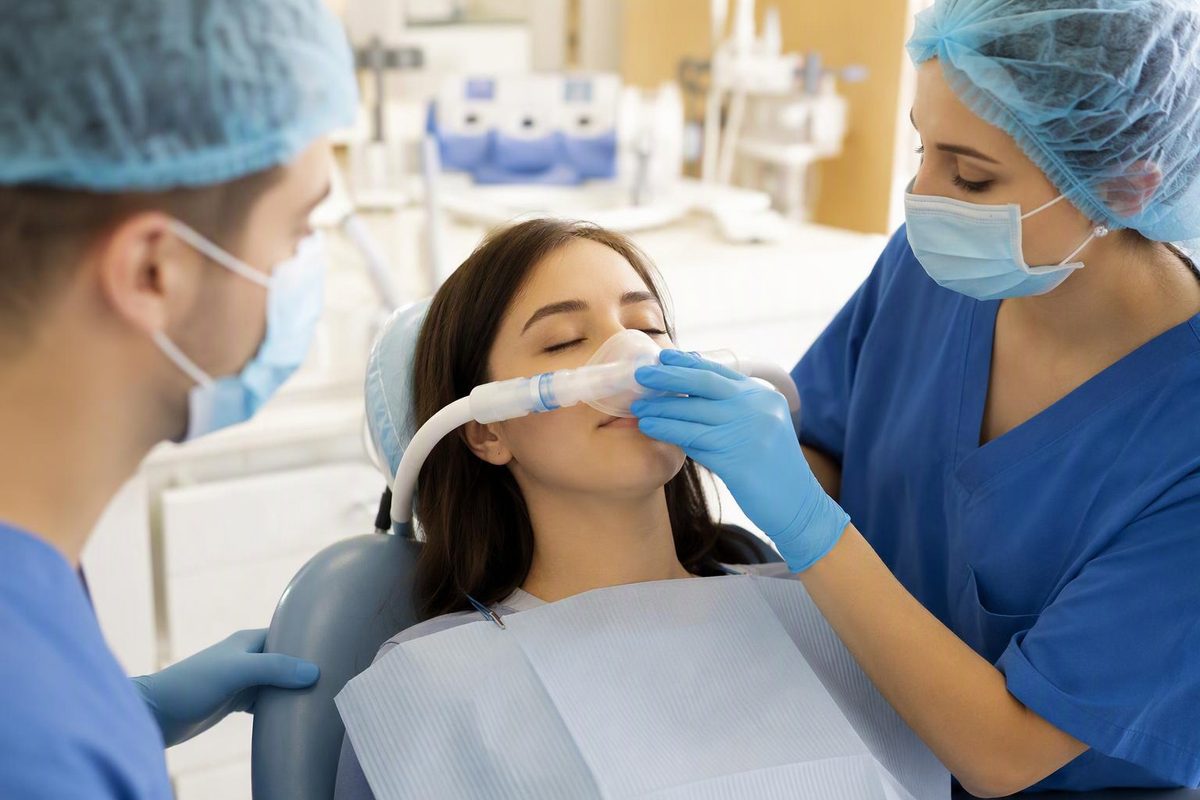
Sometimes—but being fully asleep is not required for every wisdom tooth extraction. Local anesthesia numbs the area while you stay awake. Sedation helps you relax and may make you sleepy, with little memory of the procedure. General anesthesia makes you completely unconscious. The plan depends on how difficult the extraction is expected to be, your comfort level and your health. Mayo Clinic explains these options.
The most useful question for your consultation is: “What level of anesthesia are you planning, and will I be able to respond during it?” “Being put to sleep” can mean different things.
Awake, sleepy or fully asleep: what each option means
The American Association of Oral and Maxillofacial Surgeons (AAOMS) describes the available options. The American Society of Anesthesiologists (ASA) defines the levels by how readily you respond:
| Option | What you can expect |
|---|---|
| Local anesthesia alone | Numbing injections near the tooth. You remain awake and aware. |
| Minimal sedation, such as laughing gas | You feel more relaxed but remain aware and able to answer questions. Local anesthesia numbs the extraction area. |
| Moderate sedation, sometimes called “twilight sedation” | You feel drowsy and may drift into sleep, but can respond to words or a light touch. You may remember parts of the procedure or very little. |
| Deep sedation | You are not easily awakened, but can respond purposefully to repeated or painful stimulation. You will probably have little or no memory of the procedure. |
| General anesthesia | You are completely unconscious and cannot be awakened even by painful stimulation. |
An IV is a way to give medication—not a guarantee that you will be fully unconscious. IV sedation can involve different depths of sedation. Ask about the intended level rather than relying on the word “IV” or “twilight.” The ASA’s patient guide explains that moderate sedation may leave some memories, while deep sedation usually leaves little or none.
If you stay awake, will it hurt?
Being awake is not the same as having an extraction without anesthesia. With effective local numbing, you may feel pressure and movement, but you should not feel sharp extraction pain. Sedation is commonly combined with local anesthesia, so feeling sleepy and having the gums numbed are separate parts of the plan. Mayo Clinic describes both approaches.
Before starting, agree on a signal—such as raising your hand—if you need the team to pause. If you feel sharp pain, signal promptly rather than trying to endure it.
Numbing during surgery does not mean recovery will be painless. For that distinction, see wisdom teeth removal pain by stage.
Can you ask to be asleep?
Yes. Tell the dentist or oral surgeon if being aware of the procedure worries you. You can also ask whether local anesthesia alone is a suitable option if you prefer to stay awake.
Your preference matters, but the safest appropriate plan needs an individual assessment. Procedure complexity and comfort help guide the choice; age, medical conditions and health habits can also affect anesthesia planning. Mayo Clinic and the ASA outline these factors.
Deeper sedation is not automatically better. Moderate or deep sedation can slow breathing, and deep sedation may require help keeping the airway open. The team needs to assess you and monitor you during treatment. ASA guidance explains these differences.
What to confirm before surgery day
Once you know the anesthesia plan, check these practical details:
- Eating and drinking: Get the office’s exact fasting instructions, including whether and when water is allowed. Do not substitute a general online fasting rule for your instructions. Mayo Clinic’s preparation guidance lists these questions.
- Medicines and supplements: Give the team a complete list and ask what to take that morning. Do not independently stop prescriptions or take extra calming medication; follow the prescribed dose and timing. AAOMS preparation guidance addresses medication instructions.
- Anesthesia history: Report previous problems with anesthesia and any known family history of anesthesia complications. AAOMS specifically advises sharing this history.
- Transport and support: If you will have sedation or general anesthesia, arrange a responsible adult to take you home and confirm how long someone must stay with you. AAOMS recommends a companion for transport and support for 24 hours. Ask when you may drive again; feeling awake does not replace the office’s instructions. AAOMS preparation guidance.
Before leaving the consultation, you should know the planned level, what awareness is expected, who will administer and monitor it, and what preparation you need. If the office has only said “we’ll put you to sleep,” ask them to make that more specific.